SoCS: sleep problems

I have quite a few problems involving sleep – or the lack thereof.

I often have trouble getting to sleep, staying asleep, waking up early and not being able to get back to sleep, not feeling rested after sleep. I’ve tried various things to help, all the sleep hygiene sorts of things, physician directed melatonin and medications, etc. but nothing seems to work long-term.

It seems, now that we know about my hEDS, cervical instability, Chiari, and a few more diagnoses, my sleep problems at least make sense.

One thing in particular may be due to a specific diagnosis. I developed sleep apnea a couple of years ago, although I score low on the Epworth scale. I’ve been treating it with an autoPAP, so I am breathing adequately while I sleep, which is, of course, a good thing.

One thing I wonder, though, is if I developed apnea at this time due to my Chiari malformation. One of the things that Chiari can cause is sleep apnea, so I’m wondering if, after my surgery, my sleep apnea may improve or even disappear. Sleep apnea can be caused by hEDS, though, so maybe not. It just seems odd to me because I’ve had the hEDS forever, even though it wasn’t diagnosed until this year. On the other hand, the apnea doesn’t seem to have started until the Chiari developed, obstentisibly in March ’24 when this big batch of troublesome symptoms started.

So, this post reveals one of the dangers of stream of consciousness – that the brain runs off using background info that the reader can’t follow. I’ll try to go back and put in some links that may help this make a little more sense.

It’d probably turn out better if I slept on it, but there isn’t time for that…
*****
Linda’s prompt for Stream of Consciousness Saturday this week is “sleep.” Join us! Find out more here: https://lindaghill.com/2026/08/28/the-friday-reminder-and-prompt-for-socs-august-29-2026/

One-Liner Wednesday: Chiari

When I saw the specialized neurosurgeon last week, after posting here for positive vibes, they asked what my three most troublesome symptoms are and I answered, “Brain fog, fatigue, and balance problems;” they told me that surgery for Chiari malformation should help all three, so I will have that, probably in late October.

This update is brought to you as part of Linda’s One-Liner Wednesdays series. Join us! Find out more here: https://lindaghill.com/2026/08/05/one-liner-wednesday-the-kicker/

One-Liner Wednesday: good vibe request

Tomorrow (Thursday), I will have an initial consultation with a specialized neurosurgeon in Rhode Island who may be able to address some of my health issues and would appreciate any prayers or good vibes you feel moved to offer. ❤

Join us for Linda’s One-Liner Wednesdays! Find out more here: https://lindaghill.com/2026/07/29/one-liner-wednesday-nothing/

SoCS: in a brain fog

Sometimes, I remember what I used to know and be able to do.

Sometimes, I can’t.

The brain fog from the cerebellar ectopia is perhaps being made worse by my decline in kidney function.

Or maybe by the summer weather.

Hard to say.

It’s scary, though, especially because it’s been going on for over two years now. There is hope for untangling all the underlying factors and treating them – or, at least, some of them – but probably no guarantee of getting back all my lost functionality.

Sometimes, I manage to be hopeful in a realistic sort of way.

Sometimes, not so much.

Today, not so much.
*****
Linda’s prompt for Stream of Consciosness Saturday this week is to begin the post with “Sometimes.” Join us! Find out more here: https://lindaghill.com/2026/07/17/the-friday-reminder-and-prompt-for-socs-july-18-2026/

SoCS: writing

I miss writing.

Because of the brain fog and fatigue I’ve had over the last couple of years as a result of my extra-stetchy connective tissue from my hEDS, I can’t spend as much time writing as I would like.

Some kinds of writing, like poetry, have become almost non-existent in my life. I feel like the creative side of my brain isn’t operational the vast majority of the time – and the more analytic side is only at half-capacity, at best. Heck, I have difficulty reading literature of any kind these days. I can sometimes manage to grasp poems, if it’s in the morning and they aren’t too long. I can’t read novels because I can’t get plots and characters to stick in my head over days. I can’t even manage non-fiction books because the brain fog is too thick to remember topics over the course of days and the fatigue level is such that I can’t read very long at a sitting. I’ve been trying to keep up by reading news and commentary articles and newsletters but have been so tired lately that my inbox is overflowing with unread material.

There has been so much happening here in the US that I’ve wanted to write posts about but haven’t been able to manage, which makes me sad. I keep thinking that the next specialist visit will give us something actionable to improve my condition but, instead, it usually means more tests are needed, which means waiting for the tests to be scheduled, doing them, waiting for them to be interpreted, waiting for the specialist to see the results and interpret them – which often yields a different result than the radiology reports that land in my health portal – and get back to me with what they think is going on. Then, maybe, we get to trying a treatment that may or may not work and then onto the next option or the next specialist.

I’m grateful, though, that this year I have a specialist who was finally able to diagnose my hEDS and cerebellar ectopia and that I finally have specialists who know what to try with patients like me. Unfortunately, I might need some pretty scary treatments, like brain surgery.

So, I’m grateful and scared and exhausted and anxious and tired of all the waiting and struggling and symptoms and uncertainty.

And I miss writing and being able to make it through a day without having to spend a good chunk of it lying down and being able to take walks without having someone with me in case I lose my ability to keep my balance and going to visit family and friends and being able to concentrate and speaking without having to search for the right word in some kind of frantic brain race.

I miss the life of the mind that I took for granted as part of my identity.

And here you have an illustration of why stream of consciousness writing is so dangerous to put out there, because this is a way darker post than I thought I was going to be writing when I started out with Linda’s prompt of the word miss and decided to write about missing writing.

It is, though, on brand with Top to JC’s Mind where I usually write honestly about whatever is top of mind for me, even when that mind is more scattered and glitchy and exhausted than it used to be.

There are two big imaging studies coming up for me this week and a hugely important appointment with a specialized neurosurgeon at the end of July. Meanwhile, I’m hoping against hope to get a few significant posts written here, as opposed to the last month which has not been very substantive.

Sigh.

I miss writing.
*****
Join us for Linda’s Stream of Consciousness Saturday! Find out more here: https://lindaghill.com/2026/06/19/the-friday-reminder-and-prompt-for-socs-june-20-2026/

One-Liner Wednesday: more fatigue

I’ve had a major uptick in my fatigue level so I haven’t been able to manage writing the couple dozen of posts that I wish I had over the last few weeks, but my health care team is working on a new batch of tests, a med change, and probably an additional diagnosis that may eventually lead to improvement, so stay tuned…

Join us for Linda’s One-Liner Wednesdays! Find out more here: https://lindaghill.com/2026/06/10/one-liner-wednesday-you-know-youre-tired/

on being a zebra (unicorn)

May is EDS & HSD Awareness Month. EDS stands for Ehlers-Danlos Syndrome and HSD for Hypermobility Spectrum Disorder. They are a group of inherited connective tissue disorders that remain under-diagnosed and under-treated. Case in point: I was diagnosed with hypermobile Ehlers-Danlos Syndrome (hEDS) in January at the age of 65, making sense of decades-worth of unexplained symptoms.

The Ehlers-Danlos Society uses the zebra as a symbol of the EDS/HSD community because there is a saying among the medical community that “when you hear hoofbeats, think horses, not zebras” but, sometimes, there really are zebras. Zebras also each have their unique stripe pattern, in the same way that people with EDS/HSD have their own unique presentation, depending on how their collagen and connective tissue is impacted across different body systems at that particular time in their life. The medical system in the United States and in many other countries tends to divvy medical care to specialists who only look at one body system but connective tissue disorders are easier to recognize if one takes a more integrative approach.

And a fun zebra fact: A group of zebras is called a dazzle, which leads to the Ehlers-Danlos Society saying, “Together, we dazzle!”

As I’ve continued to research hEDS, I’ve been engaging in personal forensic diagnostics. So many things I have experienced in my life make sense now that I know of my genetic inheritence of hEDS. For example, I developed tendon problems in my elbow as a young teen which impacted my abilities as a pianist and organist. When I eventually had to resort to surgery in my thirties, the outcome wasn’t as expected and I had to give up playing. I now understand that this was due to my hEDS inherited collagen defects.

My IBS, IC, endometriosis, vulvodynia, pre-term labor, allergies, mast cell activation disorder, cervical instability, near-sightedness, depression/anxiety, cerebellar ectopia, sleep apnea, early gall bladder disease, hiatal hernia, acid reflux, chronic fatigue, diverticulosis, chronic kidney disease, sensitive skin, joints that bend more than expected, and more all have a connective tissue component and are more likely in people with EDS/HSD.

Daughter T gave me the zebra unicorn pin as a gift. While the zebra is the symbol of EDS/HSD, adding the unicorn element helps to play up the uniqueness of each individual.

And it’s super cute!

The point is that another person with hEDS could exhibit a totally different set of symptoms from mine or we could share some symptoms and not others. It just depends on which connective tissues are compromised and how much at that particular time. Other factors are involved, too, like age, activity level, hormone and endocrine function, etc. It adds to the zebra-unicorn element and takes a thoughtful and informed practitioner to pick up on the possibility of an underlying connective disorder behind all the symptoms of different body parts.

In December, there will be an update to the EDS/HSD diagnostic guidelines. My hope is that the medical community will use these and the best practices guidelines that will follow in spring 2027 to finally look more comprehensively at their patients and diagnose and help them at much younger ages than currently.

Some people are also under the mistaken impression that it doesn’t do any good to give a diagnosis when you can’t cure the disorder. While it’s true that we can’t current treat the genetic cause, there are treatments to help alleviate many of the symptoms. It’s also imperative for practitioners to know the EDS/HSD status for anyone who is contemplating surgery. Surgeons need to know about connective tissue differences so that they can compensate for that during the procedure and the recovery protocols or, perhaps, decide that surgery is not appropriate. Many EDS/HSD patients also need long-term physical therapy to help them function; it makes a huge difference if physical therapists are knowledgeable about connective tissue disorders so that they help rather than hurt.

As I continue my journey with hEDS, I will keep you posted here at Top of JC’s Mind. If we are super-lucky and we find effective treatment for my brain fog and fatigue, I may even post more regularly.

I will, though, always remain my unique, zebra-unicorn self.

SoCS: sweet taste

My favorite foods are sweet.

I know that humans’ first taste preference is for sweetness. It’s why breast milk is so sweet.

Most people, though, go on to develop preferences for additional flavors. I, though, am not very tolerant of foods that are sour or bitter. Strong flavors are often physically painful for me and I’ve learned that something that most people perceive as mild are often overwhelming for me. This is especially true for hot/spicy foods, like peppers. I also don’t drink coffee or tea, which are just too bitter for me.

I wonder if this taste preference for sweet and intolerance for sour and bitter is a natural defense. One of the conditions that I have is interstitial cystitis, also known as painful bladder syndrome. (It’s probably also related to my hEDS and mast cell activation disorder, but I digress.) One of the ways to help reduce IC flares is to reduce acidic foods as much as possible. Most sour or bitter foods are also high in acid, so maybe my intolerance of those flavors is a self-defense mechanism.

By the way, salty foods are also bad for people with IC so I eat low-salt, as well. I don’t find salty foods physically painful, though, unless it is really, really, really salty, which feels like burning in my mouth.

I’m such a delicate flower!

And sweet! 😉
*****
Linda’s prompt for Stream of Consciousness Saturday this week is “sweet.” Join us! Find out more here: https://lindaghill.com/2026/05/15/the-friday-reminder-and-prompt-for-socs-may-16-2026/

SoCS: contrast

One of the many things about which I have to be careful is the use of contrast with CT or MRI scans.

We think the reason is that my kidney function is kind of flaky and the contrast agents are hard on kidneys.

The wild card is that my kidneys may be stressed because of a vascular problem related to my hEDS. I have an appointment with a specialist in NYC later this month to investigate.

Stay tuned…
*****
Linda’s prompt for Stream of Consciousness Saturday this week is “contrast.” Join us! Find out more here: https://lindaghill.com/2026/05/08/the-friday-reminder-and-prompt-for-socs-may-9-2026/

EDS/HSD Primer

May is EDS & HSD Awareness Month and I promised to do some posts on it. I had hoped to get this first post out earlier in the month but I’m having some difficulties with an hEDS flare, which has slowed me down a bit.

Ehlers-Danlos Syndrome (EDS) and Hypermobility Spectrum Disorder (HSD) are heritable connective tissue disorders. There are 13 types of EDS. In 12 of those types, the exact genetic cause has been identified. Some of these types are very rare, affecting less than one in a million people. The most common form of EDS is hypermobile (hEDS), which is known to be inherited in an autosomal dominant pattern but appears to have a more complex genetic profile. The prevalence of hEDS is unknown because it is very often missed diagnostically. Case in point, I was diagnosed at age 65.

HSD is related to hEDS, usually involving fewer hypermobile joints than most people with hEDS. While some clinicians and researchers look at HSD and hEDS as separate disroders, others look at hEDS as occupying a certain segment of the hypermobile spectrum. In December, 2026, updated diagnostic criteria will be published, with best practices to follow in spring ’27. It will be interesting to see if hEDS and HSD will be merged into a single diagnosis.

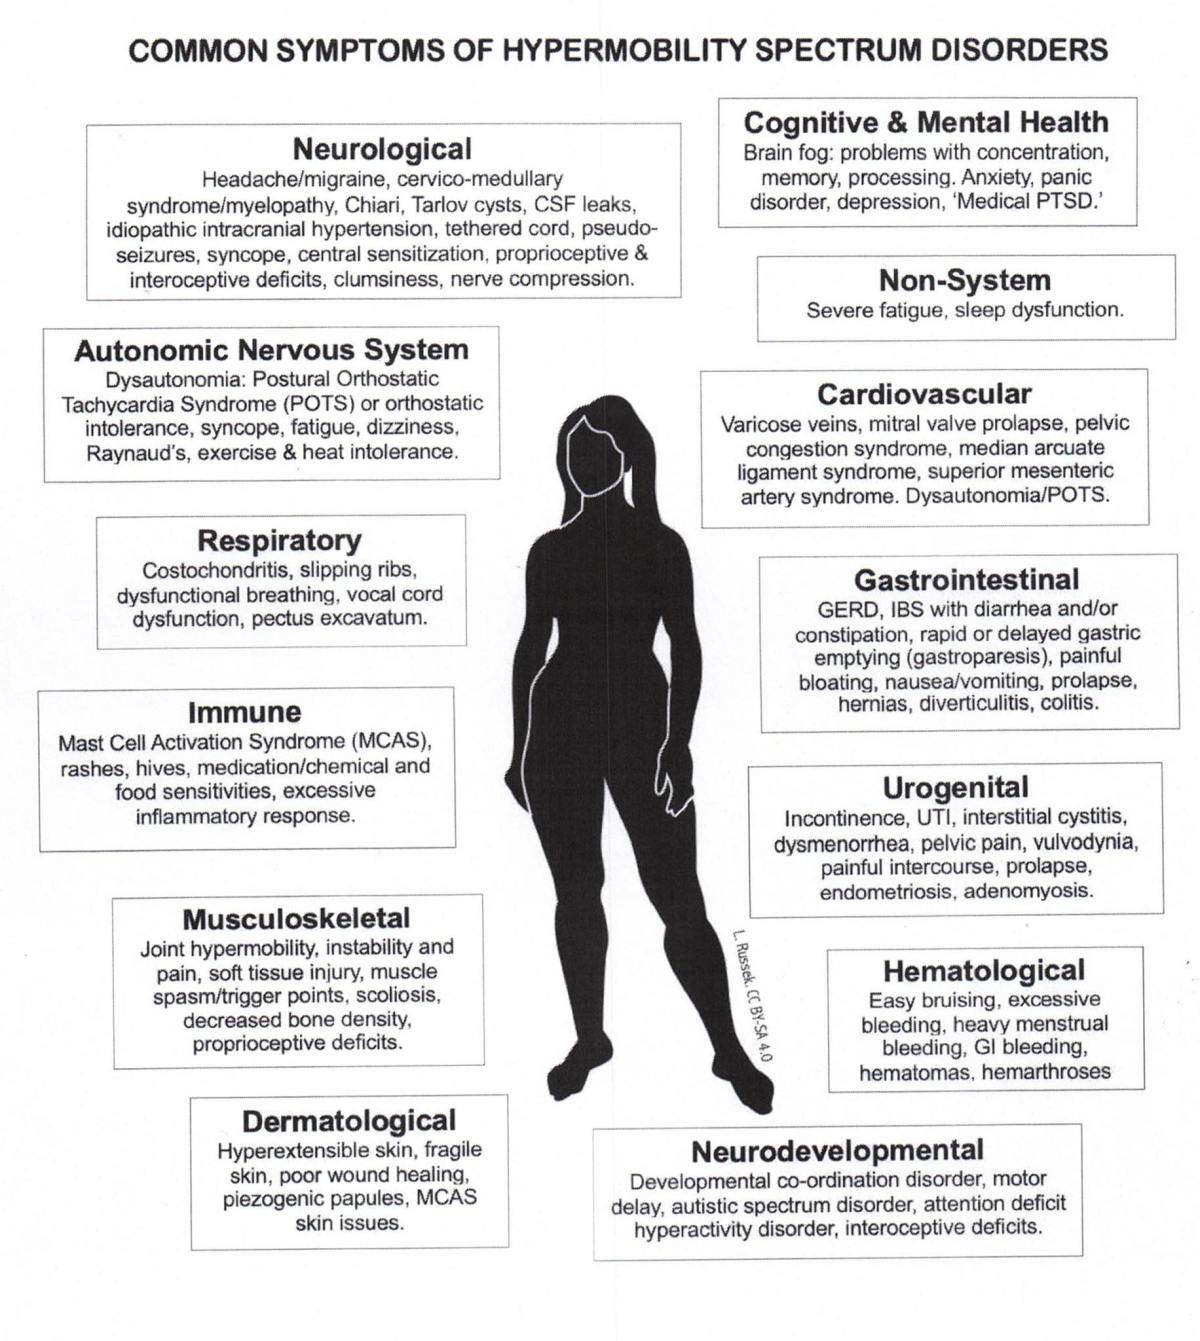
One of the difficulties with obtaining a diagnosis with EDS or HSD is that they present in different ways in different individuals and can vary with age. All forms of EDS/HSD affect connective tissue, making it stretchier than is typical, often due to genetic impacts on the proteins involved in collagen production. Symptoms appear throughout the body and in different body systems. The charts at the top gives you some idea of how wide-ranging the symptoms can be. Thankfully, no one has all the symptoms but when tends to happen in the medical systems in most countries is that you see separate specialists for different body systems and there is no one with enough knowledge to integrate all the information and realize that connective tissue is the common denominator underlying it all.

Because EDS/HSD are genetic in origin, treatment revolves around symptoms. Physical therapy is often a big part of the treatment plan. There are medications, vitamins, and supplements to help certain aspects of the disorder, too. For example, I have a mast cell activation disorder as part of my hEDS and take several medications to help relieve respiratory and gastrointestinal symptoms.

Having an EDS/HSD diagnosis also allows your care team to keep an eye out for conditions that may develop, such as heart valve problems. It’s very important for surgeons to know if your connective tissues are not typical, as this may impact how a procedure is done or if it should be done at all. How well medications work and the dosages required can also differ. For example, my hEDS diagnosis explained why topical anethetics, like lidocaine, don’t work well for me.

I am hoping that, when the new diagnostic criteria are published, there will be increased awareness of inherited connective tissue disorders among both the medical community and the general public. For too long, symptoms have been dismissed as unrelated, idiopathic, stress-induced, hormonal, anxety-induced, unimportant, or imaginary. Like autoimmune diseases, these disorders are more prevalent in females than males, adding to the burden of being taken seriously and the dearth of studies.

The Ehlers-Danlos Society is an important organization spearheading study, training, education, and treatment of EDS/HSD internationally. Their website is a great source of information for patients and their families, as well as for clinicians and researchers. This month, as we raise awareness, my hope is that more people will learn about EDS/HSD and help those affected get the diagnosis, treatment, and validation they deserve.